

Transgender Male to Female Breast Surgery
What the Male Chest Constrains
Transgender male to female breast surgery starts from the male chest, not from a chest that already has a feminine skin envelope. The overlying chest skin is tight. That tightness is the limit on how much fullness can be added in one operation if the goal is a chest that reads as feminine. A generous implant that the skin cannot cover will not sit as a breast. It will sit as an implant the skin is fighting.
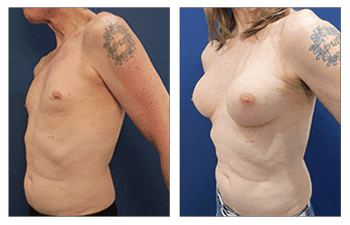
Photo legend
60-year-old transgender male underwent subfascial breast augmentation with a silicone implant to feminize her breasts.
The male breast perimeter is a straight line. The feminine outline is rounded. The operation has to convert that straight perimeter into a curve, not only add volume in the center. Nipple and areola position and size have to change as well. A fuller chest with a low, small nipple-areola complex still reads as a male chest that was filled, not as a breast whose nipple sits near the center of the mound.
The American Society of Plastic Surgeons describes breast augmentation as placement of an implant to increase breast size. The same augmentation is used here, with one change forced by the skin. The implant at the first operation is conservative. A generous size will not be accommodated by the tighter skin envelope of the male chest. Ideal placement also puts the nipple-areola complex near the center of the chosen implant. The male nipple-areola complex tends to sit lower than a female nipple and areola, so centering a large implant is not feasible. The diameter of the implant cannot outrun the nipple-to-fold distance the chest already has.
A Modest Implant First
Transgender male to female breast surgery therefore uses a more modest implant at the first stage. That implant is there to encourage the tight male chest skin to stretch. It is not the final diameter. Patients are asked to delay the second stage, an implant replacement, for a minimum of 6 to 12 months after the initial augmentation. The wait is the time the skin needs. It is not a pause added for scheduling.
During that delay the chest skin stretches, and the distance from the nipple to the inframammary crease stretches with it. A larger implant diameter needs that longer nipple-to-crease distance. Without it, the implant cannot be centered under the nipple. The second operation is a replacement with a larger implant once that distance exists, not a larger implant placed on the day the skin is still tight.
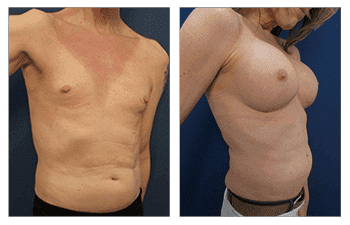
Photo legend
The service designations for this patient include Male to Female Surgery and Breast Augmentation. 60-year-old transgender male underwent subfascial breast augmentation with a silicone implant to feminize her breasts.
At that second stage, a small medially based pedicle breast lift can be added. The lift moves the nipple and areola more centrally on the mound, and it can make the areola larger so the complex looks more feminine. The pedicle is medial, so the nipple stays attached on that inner bridge while it is shifted. The lift is offered then, after the skin has stretched, not as a substitute for the first modest implant. A lift on skin that has not stretched does not create the nipple-to-crease distance a larger implant needs.
Straight Perimeter to a Rounded Outline
Fullness alone does not round a straight male perimeter. The implant has to be sized to the skin that exists, then replaced when the skin can hold more. The first mound is modest on purpose. The second mound is larger because the nipple-to-crease distance has lengthened and the nipple can sit nearer the center. The optional lift at that second stage is what repositions the nipple and enlarges the areola. Those three steps, modest implant, delayed replacement, and a small medial-pedicle lift, are the modifications of a standard female augmentation. They are how the straight line becomes a curve.
Please see this 60 years old client who was able to achieve aesthetically pleasing feminine shaped breasts.
The photographs show that result. They do not label the implant diameter at the first operation or at the replacement, and they do not label whether the medially based pedicle lift was added. A feminine shape on the photograph is the endpoint the protocol is built for. It is not proof that a large implant was placed on a tight chest in one stage. Reading the images as a single-stage augmentation misses the wait that lets the skin and the nipple-to-crease distance stretch.
How the Two Stages Are Chosen
The standing exam measures the tightness of the chest skin, where the nipple sits, and how far it is from the inframammary crease. Those three measurements pick the first implant. If the nipple is low and the crease is close, the implant stays modest so the nipple can still land near the center. A larger diameter is planned for the replacement after a minimum of 6 to 12 months, once the skin and that nipple-to-crease distance have stretched. The lift is discussed for the same second operation, when centralizing the nipple and enlarging the areola are still needed.
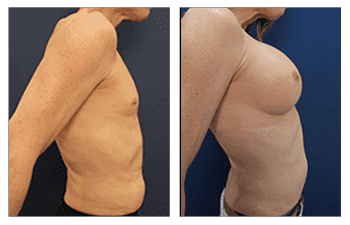
Photo legend
From this angle, the Male to Female Surgery result is easier to follow. 60-year-old transgender male underwent subfascial breast augmentation with a silicone implant to feminize her breasts.
Transgender male to female breast surgery is still a breast augmentation with those limits, not a different device and not a one-day jump to the largest implant the patient hopes for. The largest size is the one the stretched skin and the lengthened nipple-to-crease distance can center. That size is chosen at the second stage. Cost follows two operations when the replacement and the lift are both part of the plan, because the first implant is a stretcher and the second is the size the chest can then hold. The exam at the breast augmentation locations is where the first diameter is set, before either stage is promised.
A straight perimeter, a low nipple, and tight skin can all be present on the same chest. Filling only the center leaves the straight line. Lifting the nipple before the skin has stretched leaves the crease too close for a larger implant. Replacing the implant before 6 months skips the minimum this protocol uses for the skin and the nipple-to-crease distance to lengthen. The 60-year-old result is one client whose breasts read as feminine after that sequence. It is not a template that skips the modest first implant.
The Nipple Has to Land on the Implant
Centering is the reason the first implant stays small. The nipple-areola complex should land near the middle of the implant, not on its upper edge and not below it. On a male chest the nipple starts lower, and the crease is closer, so a wide implant would leave the nipple sitting on the upper half of the mound. Transgender male to female breast surgery accepts a smaller diameter until the nipple-to-crease span is long enough to put that nipple in the middle of a larger implant. Stretching the skin without lengthening that span does not solve the centering problem.
The rounded perimeter is judged the same way. A straight lower border stays straight if the implant is jammed under skin that cannot drape. After the minimum of 6 to 12 months, the replacement uses the extra skin and the longer nipple-to-crease distance to round that border. The medially based pedicle lift, when it is added, shifts the nipple toward that new center and can enlarge the areola. Skipping the lift leaves position and areola size where the male chest started, even if the volume is larger. Adding the lift at the first operation, before the crease has dropped, asks the pedicle to center a nipple over an implant the skin cannot yet cover.
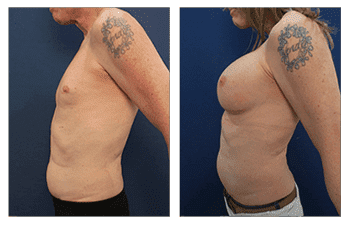
Photo legend
#SS269 is shown here in a closer clinical frame. 60-year-old transgender male underwent subfascial breast augmentation with a silicone implant to feminize her breasts.
The four clinical photographs and the 60-year-old caption belong to one client. They show a feminine shape from the front and the side views that were taken. They are not a diagram of stage one beside stage two, and they do not mark the inframammary crease or the pedicle. Use them as the shape the staged plan is aiming at. The first diameter, the wait, and whether the lift was used are decided on the chest in front of the surgeon, from skin tightness and nipple position, not from the caption alone.
Frequently Asked Questions
The male chest skin is tight, and the nipple-areola complex tends to sit low. A generous implant will not fit that envelope, and it cannot be centered on a low nipple. A modest implant lets the skin, and the nipple-to-crease distance, stretch.
After a minimum of 6 to 12 months. That delay is what lets the chest skin and the nipple-to-inframammary-crease distance stretch enough for a larger diameter. The replacement is the second stage, not a same-day upsizing.
At the second stage, a small medially based pedicle lift can move the nipple and areola toward the center of the mound and make the areola larger. It is offered after the skin has stretched. It does not replace the modest first implant.
A 60-year-old client with a feminine breast shape. They do not label implant size or whether the medial-pedicle lift was done. The shape is the result of the staged plan, not of one large implant on tight skin.
Related reading
Continue with guides on this topic, or jump to a procedure, cost, or location page.