

Does gynecomastia surgery reduce nipple size
Yes, the Nipple Gets Smaller
Does gynecomastia surgery reduce nipple size? It does. The operation decreases nipple projection, and it also reduces the areola, the flatter pink skin around the nipple. Both shrink for the same reason. The bulk under them is taken away, the pressure on that skin drops, and the skin draws back. The nipple-areola complex is not being trimmed in the ordinary case. It is being allowed to recoil.
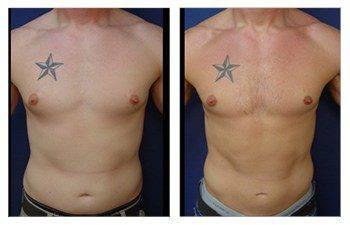
Photo legend
26-year-old male underwent Grade 3 gynecomastia surgery by undergoing direct excision of his gland and liposuction of the chest periphery.
Gynecomastia surgery removes male breast bulk. That bulk can be gland, fat, or both. How much of each is removed changes the chest contour. It does not change the reason the nipple gets smaller. Once the tissue pushing the nipple and areola forward is gone, that skin retracts and the complex looks smaller. The useful picture is a balloon. Deflate the balloon and the shell has less surface. The same drawing-in is seen routinely once the mound under the nipple is gone.
The American Society of Plastic Surgeons describes gynecomastia surgery as reduction of extra male breast tissue. On this question, that reduction is what lets the nipple and areola come down in size. Liposuction takes the fatty part at the chest periphery. Direct excision takes the gland under the nipple, which suction does not reliably clear. Leaving the gland in place leaves the pressure that was holding the nipple out. Taking only fat at the edge, and leaving the gland, is an incomplete deflation of that balloon.
The 26-Year-Old Grade 3 Chest
The first photograph is a 26-year-old man who had Grade 3 gynecomastia surgery. The operation was direct excision of the gland and liposuction of the chest periphery. That pairing is the ordinary way the pressure under the nipple is removed: the gland comes out through an excision, and the fatty rim of the chest is suctioned so the periphery does not stay full after the center is flat. Grade 3, on this case, is that combination. It is not a skin excision around the areola.
The later photographs are a 34-year-old man after bilateral gynecomastia repair. Both sides were treated, so the nipple and areola on each side had the bulk under them removed. The captions do not measure the areola before and after in centimeters. They show the repair. The expected change, when elastin is still present, is a smaller, less projecting nipple and a smaller areola, because the skin recoiled after the pressure dropped. A repair that leaves one side's gland behind will leave that nipple more projected than the side that was fully excised.
Elastin Decides How Far the Skin Recoils
Skin quality changes how much smaller the nipple and areola become. Elastin is the rubber-band protein in skin. It is what recoils the skin once the pressure under it is gone. With age, elastin density is lost. Typically, by 45 years of age, no elastin is left. A 50-year-old client will not see the same reduction in nipple and areola size as a 20-year-old. The gland and the fat can still be removed at 50. The shell simply will not shrink the way a younger shell does. That is a limit of recoil, not a sign that the gland was left behind.
The 26-year-old and the 34-year-old are both well under that 45-year mark, so their skin is in the group that can still retract after the mound is removed. Their photographs are not a prediction for a chest that has already lost its elastin. Comparing a young result with an older chest, and expecting the same areola shrink, ignores the protein that does the shrinking. Removal of bulk is the same operation. The recoil is not.
When the Areola Itself Has to Be Cut
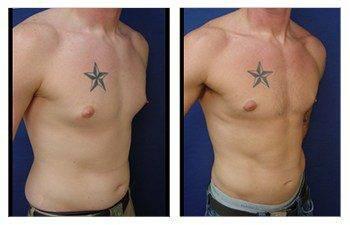
Photo legend
The service designations for this patient include Gynecomastia / Male Chest. 26-year-old male underwent Grade 3 gynecomastia surgery by undergoing direct excision of his gland and liposuction of the chest periphery.
A rare chest has a nipple and areola that are extensive in size to begin with. Recoil after the gland comes out may not be enough, even in younger skin. The same shortfall happens when the patient is much older and elastin density is already gone. In either situation, a separate peri-areolar reduction can be added. Actual areola skin is excised circumferentially, in a ring, so the remaining areola is smaller. That cut is more aggressive than waiting for recoil, and the incision line around the areola is more noticeable than the access used only to take the gland out.
The peri-areolar excision is done during the gynecomastia surgery, not as a later mystery. It is a supplement for the extensive areola or for the chest that will not recoil. It is not the default for a Grade 3 chest in a 26-year-old, whose gland excision and peripheral liposuction are expected to let the nipple draw in on their own. Adding a circular incision when recoil would have been enough trades a smaller areola that was going to happen anyway for a scar the patient can see.
Does gynecomastia surgery reduce nipple size without that extra cut? Yes, when elastin can still retract the skin after the gland and fat are gone. Does gynecomastia surgery reduce nipple size when the areola is already extensive, or when elastin is gone after about 45? The removal of bulk still flattens the mound, and the formal peri-areolar excision is what makes the areola smaller than recoil alone will allow. Those are two different amounts of reduction, and they leave two different incisions.
What the Exam Is Choosing
The standing exam separates gland from fat, looks at how far the nipple projects, and looks at how wide the areola already is. A firm mound under the nipple is gland and needs excision. A soft fullness at the chest periphery is fat and needs liposuction. A wide areola on a young chest may still shrink once that pressure is gone. A wide areola on a chest past the age when elastin is gone will not, and the peri-areolar cut is discussed then. The 26-year-old Grade 3 case and the 34-year-old bilateral repair are the recoil path. They are not pictures of a circumferential areola excision.
Cost follows whether the plan is gland excision plus peripheral liposuction, or that operation plus a peri-areolar skin excision. The second cut is more aggressive and more visible. It is added for size that recoil will not fix, not as a routine circle on every chest. The exam at the gynecomastia locations is where skin age, areola width, and how much of the bulk is gland are called, before either incision is promised. Does gynecomastia surgery reduce nipple size in both plans? It does. One plan lets the skin shrink. The other also cuts areola skin away.
Gland and fat are told apart on the chest, not from the photograph captions. A discrete firm disc under the nipple is the gland that direct excision removes. A softer layer spreading toward the axilla and the lower chest fold is the periphery that liposuction treats. Doing only the disc, and leaving the periphery full, flattens the nipple and leaves a wide chest. Doing only the periphery, and leaving the disc, lets the nipple stay propped up. The Grade 3 operation on the 26-year-old did both. The bilateral repair on the 34-year-old did both sides. Neither print is a measuring tape on the areola, so the shrink is judged by looking at projection and areola width on the standing chest, not by a number the captions never give.
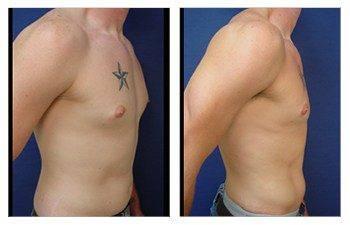
Photo legend
From this angle, the Gynecomastia / Male Chest result is easier to follow. 26-year-old male underwent Grade 3 gynecomastia surgery by undergoing direct excision of his gland and liposuction of the chest periphery.
The circular incision is the one patients can see in a mirror, which is why it stays off the plan unless recoil will fail. A young chest with an areola that is large only because it is stretched over gland will usually gather once that gland is out. An extensive areola that is large even aside from the stretch, or a chest past the loss of elastin, will not gather enough. Those are the chests offered the ring of excised areola skin. The scar is the cost of a reduction the balloon effect cannot finish.
Frequently Asked Questions
Yes. Removing the gland and fat under the nipple drops the pressure on the areola as well as on the nipple. When elastin is still present, that pink skin retracts and looks smaller. It is the same recoil, not a separate trim.
Elastin is what pulls the skin back. Typically, by 45 years of age, that elastin is gone. A 50-year-old will not see the nipple and areola reduction a 20-year-old sees, even after the same gland excision. The mound is flatter. The shell does not gather as much.
A circumferential excision of areola skin, done during the gynecomastia surgery when the areola is extensive or when elastin will not recoil. It reduces size more aggressively and leaves a more noticeable incision around the areola.
The 26-year-old had Grade 3 surgery: direct excision of the gland and liposuction of the chest periphery. The 34-year-old had a bilateral repair. Neither caption describes a peri-areolar skin excision. Both are in the age range where recoil can still shrink the nipple.
Related reading
Continue with guides on this topic, or jump to a procedure, cost, or location page.