

Safe BBL Protocol
Why the Safe BBL Protocol Exists
The Safe BBL Protocol is a set of steps meant to lower the risk of fat emboli during a Brazilian butt lift. The risk comes from fat entering a vein under the gluteus maximus, the largest glute muscle. Those superior gluteal veins sit deep in the pelvis, beneath the muscle. Fat that reaches them can travel to the lungs. Every step below is aimed at one result: fat grafting stays in the subcutaneous fat, and the cannula does not enter the muscle or the space under it.

Photo legend
70-year-old female following improvement in buttock contour with liposuction of the upper lateral buttocks and flanks followed by fat grafting to the lower lateral buttock region to improve her overall proportions.
Surgeons already know that grafting fat into this deep region can be harmful. The emboli that still occur are explained by a cannula that bends, a tip that is not felt, a deep landmark that is missed, or fatigue late in the day. The Safe BBL Protocol treats each of those as a separate control, not as one general warning.
Fat Stays in the Subcutaneous Layer
Fat is transferred only into the subcutaneous layer. There is no intramuscular injection and no submuscular injection. The stiff cannula, the landmarks, the ultrasound check, the level hand, and the limit on how many cases are done in a day all exist to hold that plane. Projection of the buttock comes from fat placed above the muscle. It does not come from filling the muscle.
A pass that starts in fat and then dips under the fascia has left the Safe BBL Protocol, even if most of the graft looks superficial. The plane is judged at the tip, not by the average of the pass.
A Stiff Cannula That Can Be Felt
The tip has to stay out of the gluteus maximus and out of the space under it. Two features of the cannula make that possible. The cannula is stiff and rigid, so it does not bend, and it is palpable through the skin. It is also at least 4mm in caliber, which adds to that stiffness and makes the shaft easier to feel. A thin, flexible cannula can drift deep while the hand still feels as if it is in fat.
The fat is collected by liposuction before it is grafted. On the case above, that liposuction was of the upper lateral buttocks and flanks, the waist and hip harvest, and the graft went to the lower lateral buttock. Harvest and graft are different steps. Liposuction does not choose the plane. The cannula that returns the fat does.
The Bermuda Triangle
Glute anatomy is what keeps the tip away from the superior gluteal vein. One landmark is the Bermuda triangle. It is the triangle drawn from the venous dimple, the greater trochanter, and the coccyx. The venous dimple is the skin dimple made by cutaneous ligaments that reach the posterior superior iliac spine. Grafting inside this triangle, deep to the fat, is the path toward the vein. The Safe BBL Protocol uses the triangle as a region with no deep pass.
The Mendieta Guideline
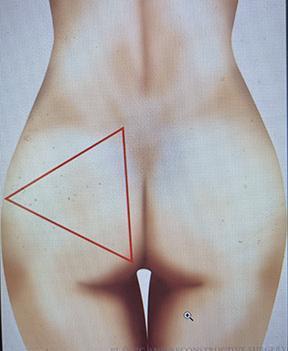
Photo legend
A close-up following the Safe BBL Protocol.
The Mendieta guideline marks a second danger area. It sits just medial to a line drawn from the lateral side of the PSIS dimple to the lateral side of the ischial tuberosity. Vertically, it is halfway between the sacral dimple and the coccyx. A cannula aimed at that point from a low port is aimed at the vein, even when the hand feels as if it is still in fat. The guideline is a map, used with the Bermuda triangle, not a substitute for feeling the tip.
Small Aliquots, Placed Only on the Way Out
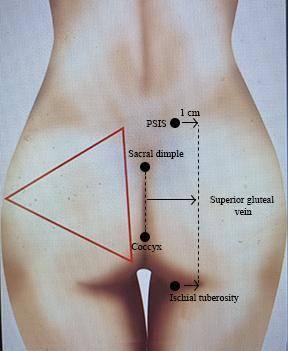
Photo legend
A diagram of a woman's body following Safe BBL Protocol.
Grafting follows the pattern used for filler in the face: small amounts, and only while the cannula is coming back out. In the face, that pattern limits filler emboli into the angular artery and then the ophthalmic artery. In the buttock, the same pattern keeps a large deposit from sitting in one spot near a vein. The Safe BBL Protocol does not treat a large bolus, pushed in while the cannula is advancing, as an acceptable pass.
Where Ultrasound Fits in the Safe BBL Protocol
Ultrasound is used to see the cannula during fat grafting. Cannulas made to show up on ultrasound let the surgeon see the shaft. The fat being placed is harder to see than the cannula. Ultrasound does not replace a stiff cannula or the landmarks. It checks them.
There is a real limit. The surgeon cannot watch the ultrasound monitor and the buttock at the same time. Because of that limit, ultrasound is used to learn the lay of the tissue, and it is used in the areas near the expected path of the superior gluteal vein. It is not a reason to look away from the cannula for the rest of the case. The pictures below show the surface landmarks and the ultrasound view used for that check.
Keeping the Cannula Level
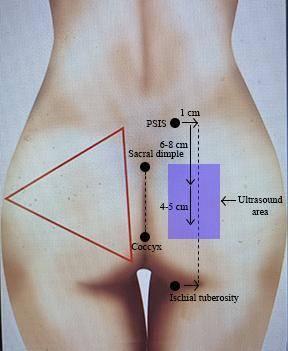
Photo legend
A diagram of a woman's body following the Safe BBL Protocol.
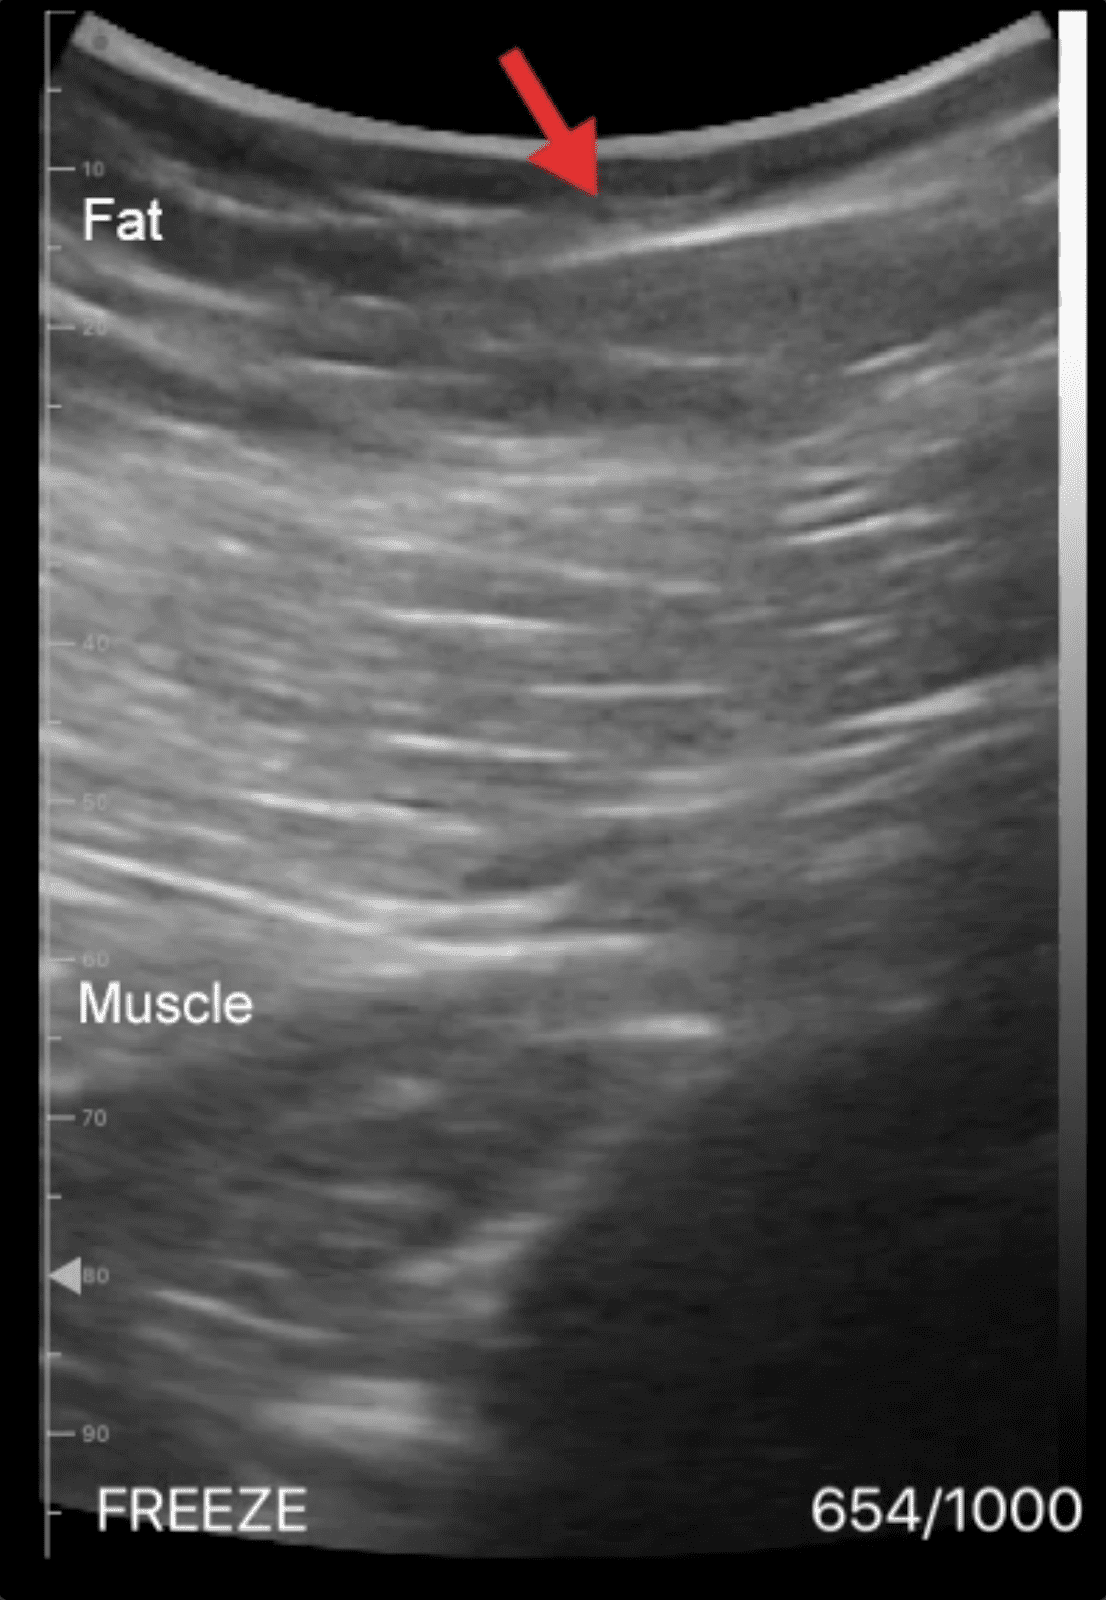
Photo legend
A close-up of an ultrasound following the Safe BBL Protocol.
Keeping the cannula level holds the tip high, away from the deep buttock where the superior gluteal vein lies. The hand that holds the cannula stays down. With an infra-gluteal port, drapes or a bear hugger can force that hand up, and a raised hand aims the tip down. A cannula that is not bulky, and that does not have the hose attached at its base, is easier to keep level. Both designs make it harder to point the tip downward by accident.
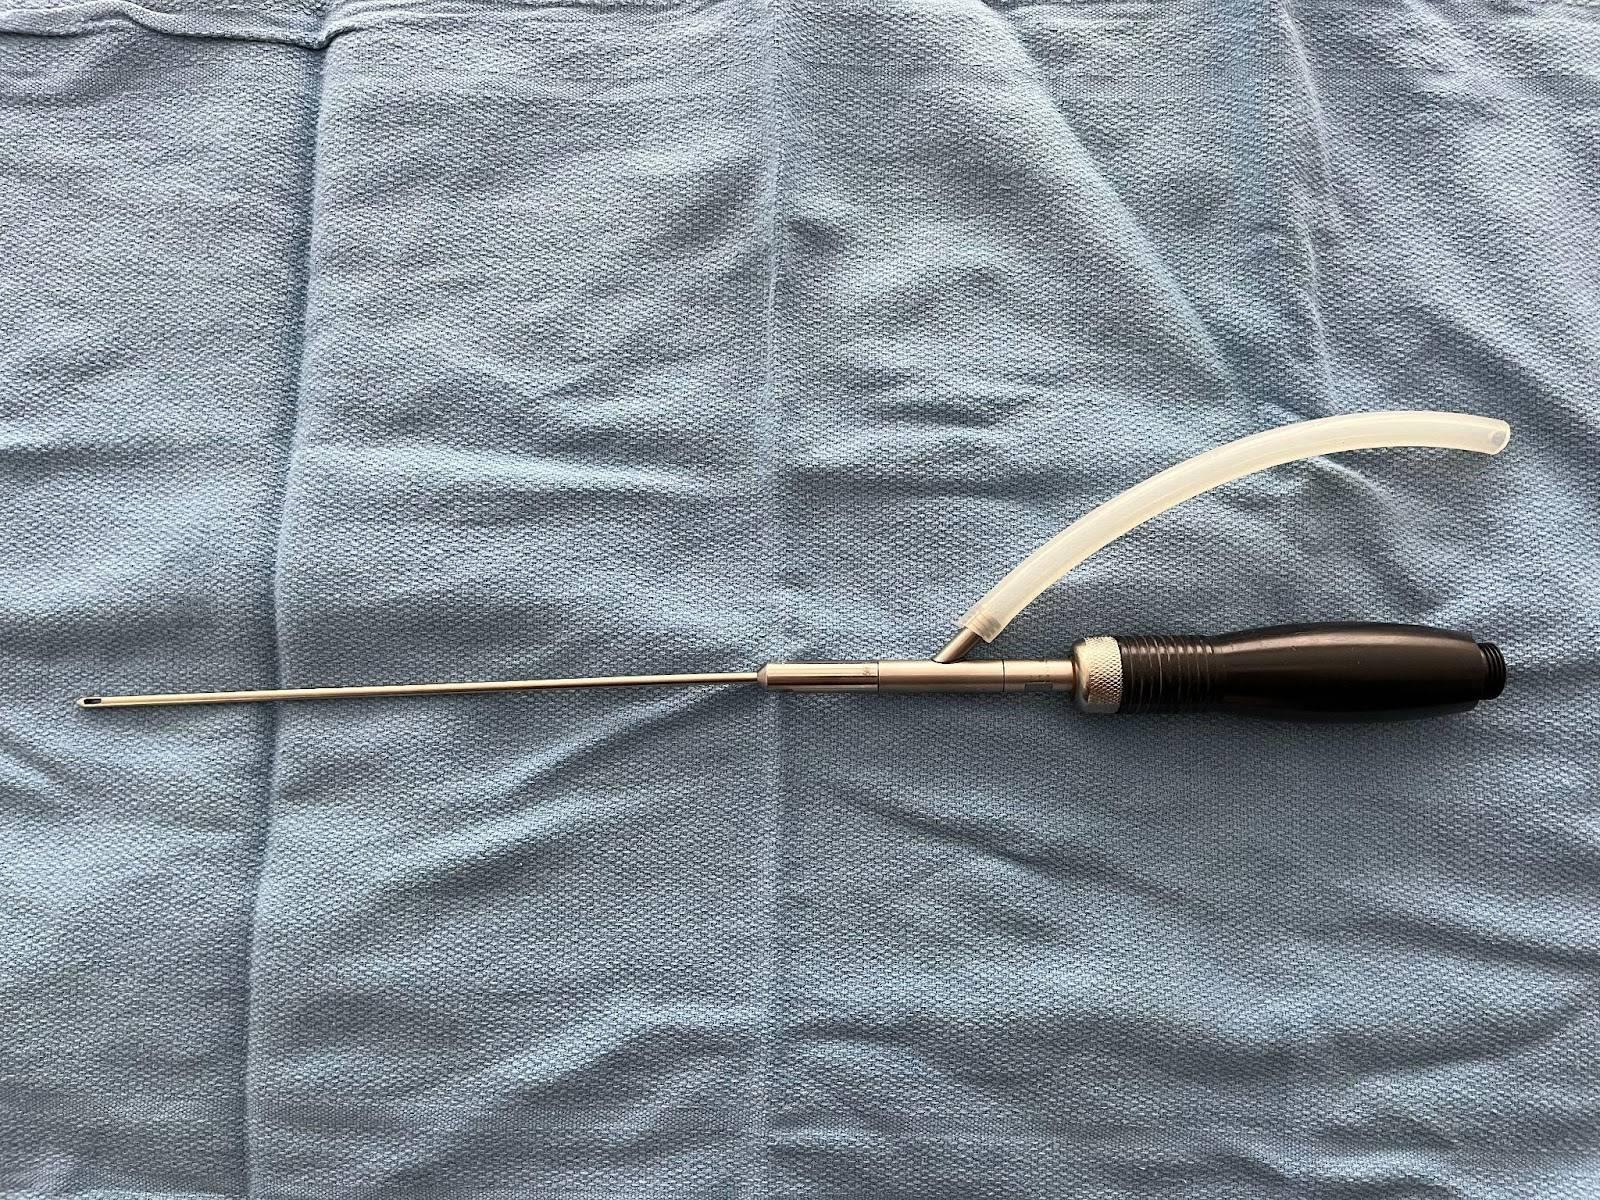
Photo legend
A needle with a tube on a blue cloth for Safe BBL Protocol.
If the port is infra-gluteal, it is placed more lateral so the hand is not fighting the drapes. The bed is placed in a gentle anti-flex position of 10 degrees, which drops the deeper zone away from the tip. Grafting from the opposite side is harder than grafting from the same side when the port is under the fold, and that reach is another way the tip drifts deep. Some surgeons therefore limit the port to the sacral zone, where a deep pass is harder to make. The port site is part of aiming.
Why the Day Is Capped at Three Cases

Photo legend
A medical table with a black cover on it, following the Safe BBL Protocol.
Another proposed cause of fat in the muscle is strain and surgeon exhaustion. Review of fat emboli cases found more of them later in the day, in a surgeon's later cases. The Florida Medical Board treated that pattern as a reason fatigue can lead to an intramuscular injection. A joint safety statement describes that Florida response. The board's limit is 3 cases per surgeon per day, meant to cut that exhaustion.
The exact number is less important than the fatigue it is meant to prevent. A tired hand lets the tip drift into the deeper buttock. The same drift shows up when the reach is awkward, which is why the opposite side is harder from an infra-gluteal port. Stopping before that fatigue, and choosing a port that does not force a deep angle, are both part of keeping the tip in fat.
Volume and the Superior Gluteal Vein
One explanation of emboli does not require the cannula to be inside the vein. Fat placed in the buttock can swell and tether the vein that runs under the gluteus maximus. The space under that muscle is loose and can stretch, in the way a subpectoral pocket can stretch. If the vein tears, blood moving through it can create a sucking pressure, which is Bernoulli's description of flow at different speeds. Fat particles near the tear can be drawn in.
Higher volumes could mean more swelling, a greater chance of that tear, and more fat near the vein if any fat has strayed deep. Volume has not been shown to be a proven risk factor. It is still treated as a practical limit, along with the separate risks of fat necrosis, a blowout, and too much pressure on the skin. The working limit in this protocol is less than 1500cc in each buttock.
Two Florida actions sit behind the Safe BBL Protocol. The first made injection of fat into the gluteus muscle a criminal act. The second, passed in June of 2022, was an emergency rule that limited surgeons to no more than 3 Brazilian butt lift surgeries a day and required ultrasound for those cases. Subcutaneous placement, a cannula that can be felt, the landmarks, a level hand, and a day that stops before fatigue are how those rules are carried out in the operating room.
Frequently Asked Questions
No. Fat stays in the subcutaneous layer. Intramuscular and submuscular injection are excluded. The cannula, the landmarks, and the ultrasound check are there to keep the tip in fat and out of the gluteus maximus.
A cannula of at least 4mm is stiff enough to resist bending and large enough to feel through the skin. A thinner cannula can flex and enter the muscle while the hand still senses fat. Feeling the shaft is how the tip is known to be shallow.
Fat emboli in the cases that were reviewed clustered later in the day. Fatigue was taken as a cause of a tip that drifts deep. The Florida limit of 3 Brazilian butt lift cases per surgeon per day is the control aimed at that fatigue. An awkward reach to the opposite side from a low port is treated as the same kind of drift.
No. Ultrasound shows the cannula, and it shows the fat less clearly. The surgeon cannot watch the monitor and the buttock at the same time, so ultrasound is used to map the tissue near the superior gluteal vein. The stiff cannula, the Bermuda triangle, the Mendieta guideline, and a level hand still do the work of staying in the subcutaneous layer.
Related reading
Continue with guides on this topic, or jump to a procedure, cost, or location page.
- BBL Meaning: What BBL Stands For (Brazilian Butt Lift)BBL / Booty
- Safe BBLBBL / Booty
- Am I Too Thin for a Skinny BBL?BBL / Booty
- Are You Too Thin for a Skinny BBLBBL / Booty
- Avoid Wells Johnson Cannister With One BBLBBL / Booty
- BBL Complications Years LaterBBL / Booty
Source: /safe-bbl-protocol/